Live AI Dream Session, Vol. 3: Trustworthy AI in Practice with Sarath Kuravi and Dr. Shonraj Ballae • Nov 10 | 11:00 AM EST Reserve Your Seat Claim Free Seat

Reserve Your Seat

MLOps in Healthcare and Pharma: How Teams Govern Models in Production

A model that classifies adverse event reports or stratifies patient risk becomes a regulated computerized system the day it goes live, with one complication that conventional validation never had to absorb: its performance depends on data it has not seen yet. The records it produces still carry the same integrity, traceability, and privacy obligations as a batch record or a claims file. MLOps in healthcare and pharma is the discipline that keeps those two facts aligned, so that every model in production can be reproduced, explained, and defended at inspection.
Machine learning operations (MLOps) already gives teams the raw mechanics: pipelines, experiment tracking, model registries, and monitoring. This guide covers what healthcare and pharma teams add on top of those mechanics, stage by stage, building on our broader guide to MLOps for regulated industries.
What is MLOps in healthcare and pharma?
MLOps in healthcare and pharma is the practice of running machine learning pipelines so every production model can be reproduced, explained, and defended at inspection. It adds regulated controls to standard MLOps: validated releases, Part 11 audit trails, HIPAA safeguards, and change control that is approved before retraining begins.

Key Takeaways

Which Regulations Apply to MLOps in Healthcare and Pharma?

No single regulation governs machine learning (ML) in healthcare and life sciences. Teams assemble their obligations from records rules, privacy law, the good practice regulations collectively known as GxP (manufacturing, clinical, laboratory, and pharmacovigilance), and artificial intelligence (AI) guidance that is still maturing. The documents below carry the most weight for models in production.
Source Status What it asks of the pipeline
21 CFR Part 11 (Code of Federal Regulations) Binding regulation Validated systems, secure time-stamped audit trails for record creation, modification, and deletion, and change control over systems documentation[1]
Health Insurance Portability and Accountability Act (HIPAA) Security Rule, 45 CFR 164.312 Binding regulation Access control, integrity safeguards, and audit controls that record and examine activity in systems holding electronic protected health information (ePHI)[2]
U.S. Food and Drug Administration (FDA) guidance on AI for drug and biological decision-making, January 2025 Draft, nonbinding A risk-based credibility assessment for a defined context of use, with life cycle maintenance after deployment[3]
FDA and European Medicines Agency (EMA) Guiding Principles of Good AI Practice, January 2026 Joint principles Traceable data provenance in line with GxP, risk-based performance assessment, and scheduled monitoring for issues such as data drift[4]
FDA Predetermined Change Control Plan (PCCP) guidance for AI-enabled device software Final, nonbinding Pre-specified modifications, a protocol to develop, validate, and implement them, and an impact assessment[5]
European Union (EU) Good Manufacturing Practice (GMP) Annex 22, Artificial Intelligence Consultation draft Continuous oversight of AI systems, including change control, performance monitoring, and human review procedures[6]
The practical reading of the table is that Part 11 and HIPAA are enforceable today, while the AI-specific documents describe the evidence inspectors will increasingly expect to see. FDA AI compliance in 2026 therefore means satisfying binding records and privacy rules with evidence organized the way the AI guidance describes it.

How Does FDA’s Context of Use Shape AI Model Validation?

FDA’s draft guidance anchors validation to a defined question and a context of use (COU), then rates model risk on two factors. Model influence is the weight the model’s output carries in the decision relative to other evidence. Decision consequence is the significance of an adverse outcome if that decision turns out to be wrong.[3]
The guidance’s own example of high risk on both counts is a model used to decide which trial participants can skip inpatient monitoring after dosing. A model that ranks literature for a human reviewer would sit far lower, and its credibility plan can be lighter in proportion.
This framing answers how FDA expects AI models to be validated and monitored in clinical settings: through evidence scaled to risk, defined before deployment, and maintained for as long as the model is in use. Operationally, the COU statement, risk rating, and acceptance criteria belong in the model registry as metadata on every version. When an inspector asks why a model was validated the way it was, the answer then travels with the model rather than sitting in a document nobody can locate.

How to Govern MLOps in Healthcare and Pharma, Stage by Stage

Implementing MLOps in healthcare and pharma comes down to deciding what evidence each stage must produce, then making the pipeline produce it automatically.

How Is MLOps in Healthcare Different From Standard MLOps?

Standard MLOps and its regulated form share the same tooling. The difference is the evidence each step has to leave behind.
Area Standard MLOps MLOps in healthcare and pharma
Data Versioned datasets Immutable, hashed snapshots linked to each model version, with ePHI kept in access-controlled zones and de-identified before experimentation
Validation Metrics reviewed after training Acceptance criteria fixed before training, tested on held-out data, with the report assembled from pipeline metadata
Release Automated promotion to production An approval signature bound to a specific model version, with a Part 11 audit trail of who approved what and when
Monitoring Drift alerts Thresholds set by the COU risk rating; a breach opens a quality investigation with documented root cause
Retraining Scheduled or triggered automatically A retraining protocol or PCCP, approved in advance, covering triggers, data windows, acceptance criteria, and rollback
Accountability The ML team A named owner, risk tier, and review date in a model inventory, with human review of AI outputs that inform regulated decisions

Stage 1: Data Preparation and Provenance

The FDA and EMA principles ask that data provenance, processing steps, and analytical decisions be documented in a traceable, verifiable manner consistent with GxP.[4] In practice, every training set becomes an immutable, hashed snapshot that a model version points to, so retraining on identical data is always possible. A HIPAA-compliant ML pipeline adds two controls at this stage: ePHI stays inside access-controlled zones with logged activity, and data is de-identified before it reaches experimentation environments that have no need for identifiers.

Stage 2: Training and Validation

GxP MLOps for pharma uses the same automation as conventional MLOps, operated under a risk-based quality system so the automation itself generates the evidence. Each training run captures the code commit, container image, parameters, and dataset version without manual entry. Performance is tested against acceptance criteria fixed before training, on held-out data the team did not tune against, and the validation report is assembled from pipeline metadata instead of being written after the fact.

Stage 3: Release and Approval Under Part 11

Promotion from staging to production is where 21 CFR Part 11 AI validation concentrates, starting with validation of the systems involved (§11.10(a)). The promotion is an electronic record: it needs an approval signature bound to a specific model version (§11.70), and an audit trail showing who approved what and when (§11.10(e)). Part 11 also requires change control over systems documentation (§11.10(k)), which in an MLOps setting extends to pipeline definitions and infrastructure code.[1]

Stage 4: Production Monitoring and Drift

Monitoring covers three signals: shifts in input distributions, shifts in output distributions, and realized performance once ground truth arrives, such as adjudicated adverse event cases or confirmed readmissions. In healthcare MLOps, alert thresholds should follow the COU risk rating. A breach opens an investigation under the quality system with documented root cause, which keeps automatic retraining from silently masking a problem. Prediction logs are records in their own right and need retention periods aligned with the underlying regulation.

Stage 5: Change Control and Retraining

Every retrained model is a new version, and the pharma AI model lifecycle depends on deciding in advance how much revalidation each type of change requires. For AI-enabled medical devices, a PCCP lets manufacturers describe planned modifications, the methodology to develop, validate, and implement them, and an assessment of their impact, so pre-authorized changes do not each need a new marketing submission.[5] The draft EU Annex 22 points in the same direction for manufacturing, pairing change control with ongoing performance monitoring.[6] The retraining protocol, covering triggers, data windows, acceptance criteria, and rollback, should be approved before the first deployment rather than drafted during the first incident.

Evidence Each Stage Must Produce

The table below summarizes what the pipeline should generate at each stage, and which requirement drives it.
Stage Evidence the pipeline must produce Main driver
Data preparation Hashed, immutable training data snapshots tied to each model version, logged ePHI access, and de-identified data for experimentation FDA and EMA principles; HIPAA Security Rule
Training and validation Code commit, container image, parameters, and dataset version for every run, plus results against pre-set acceptance criteria GxP risk-based quality system
Release and approval An approval signature bound to the model version, an audit trail of approvals, and change control over pipeline and infrastructure code 21 CFR Part 11
Production monitoring Input, output, and performance monitoring records, investigation records for threshold breaches, and retained prediction logs FDA draft AI guidance; FDA and EMA principles
Change control An approved retraining protocol or PCCP, and revalidation evidence for every new model version FDA PCCP guidance; draft EU Annex 22
Not sure your retraining protocol would hold up at inspection? Book a governance gap review.

Why Is Human Oversight Required for AI in GxP Settings?

In an April 2026 warning letter, FDA stated that when a manufacturer uses AI to help with current good manufacturing practice (CGMP) activities, any output or recommendation from an AI agent must be reviewed and cleared by an authorized human representative of the firm’s quality unit.[7] That case involved AI-drafted specifications and procedures rather than a deployed predictive model, yet the principle carries over directly: accountability for an AI-assisted decision stays with named people.
The FDA and EMA principles reinforce this by asking that performance assessment cover the complete system, including human and AI interaction.[4] For MLOps teams, that translates into review queues for low-confidence outputs, explanations surfaced at the point of review, overrides captured in the audit trail, and override rates tracked as a monitoring signal in their own right. Sound model governance for healthcare AI wraps these controls in a model inventory that records an accountable owner, a risk tier, and a periodic review date for every model in service.

How Intuceo supports governed MLOps

Intuceo is a PhD-led AI, ML, and data analytics services firm whose life sciences work includes Janssen, Ferring Pharmaceuticals, and Bausch & Lomb. Its MLOps engagements build compliance into the pipeline from the first commit, so audit logs, lineage, and validation evidence accumulate through normal operation. Deployed models carry drift monitoring, controlled retraining loops, and interpretability views designed for the reviewers who sign off on outputs.
Explainability, bias checks, and model documentation are reviewed by Intuceo’s PhD-led Board of Science & Innovation, and the iPDLC™ delivery framework places PhD-led quality gates at every transition from development to production. Teams work across MLflow, Kubeflow, and Amazon SageMaker, so governance fits the stack a client already runs instead of forcing a migration.
Running models in production ahead of an inspection or a submission? Get a governance gap review that maps each model to its context of use, audit trail coverage, and change control readiness.

Frequently Asked Questions

Pharma companies govern ML models under Part 11 by first scoping which ML artifacts count as regulated records. FDA’s Part 11 scope and application guidance ties the rule to records that other regulations, known as predicate rules, already require. It also describes enforcement discretion for certain Part 11 requirements, while predicate rule obligations stay fully in force.[8] Pharma teams therefore classify ML artifacts individually. Model outputs that feed a GxP decision, validation reports, release approvals, and training data cited in a submission are typically treated as regulated records. Exploratory notebooks stay outside scope until their results become the basis for a regulated decision.
It looks like a validated computerized system whose validation never fully closes. The International Society for Pharmaceutical Engineering (ISPE) Good Automated Manufacturing Practice (GAMP®) Guide: Artificial Intelligence was published in July 2025 for use alongside GAMP 5 (Second Edition). It covers the AI-enabled system life cycle, the responsibilities of internal and external suppliers, and ongoing monitoring and maintenance.[9] Two practical consequences follow. Cloud ML services used in GxP work need supplier assessment and infrastructure qualification. GxP and non-GxP workspaces should also be kept separate, so exploratory work cannot reach production without passing through change control.
Healthcare organizations keep ML pipelines HIPAA-compliant by de-identifying data, scrubbing identifiers from ML outputs, and holding business associate agreements (BAAs) with vendors. Most start by deciding which de-identification route applies. HIPAA recognizes two: removing a specified list of identifiers, or a formal determination by a qualified expert applying statistical and scientific methods.[10]
Beyond that, the most common leak path in healthcare MLOps is incidental. Identifiers get written into experiment logs, prediction logs, feature store snapshots, or error traces. Most of the gaps teams find in audits close with three steps: scrubbing those outputs, keeping features to the minimum the model needs, and holding BAAs with any vendor that touches ePHI.
A typical pharma MLOps stack has five layers:
Whatever tools you choose, the configured system, including its procedures, access controls, and retention settings, must be validated. That is why tool selection should follow the governance design rather than come before it.
A PCCP lets makers of AI-enabled medical devices pre-specify planned model modifications, the protocol to develop, validate, and implement them, and an assessment of their impact. Once FDA authorizes the plan, changes made within it do not each need a new marketing submission.[5] For MLOps teams, the PCCP becomes the approved rulebook for retraining.

HEDIS Care Gap Closure in Florida: How Payers Use AI to Improve Star Ratings

Every open care gap in a Florida health plan carries two costs at once. One is clinical: a member who missed a screening or a chronic-care check. The other is financial: a quality measure that slips below its threshold and pulls down a rating tied to millions in federal payments.
Both costs come due at the same moment. When the measurement year closes, the numbers lock, and the window for HEDIS care gap closure shuts with them. The Healthcare Effectiveness Data and Information Set (HEDIS), maintained by the National Committee for Quality Assurance (NCQA), defines most of those measures. Its results feed the Medicare Advantage (MA) Star Ratings, and those ratings decide quality bonus dollars.
Florida concentrates the problem more than most states. It carries one of the country’s largest Medicare Advantage populations. It runs a Medicaid managed care program that holds plans for their own quality reporting. And its membership spreads across languages and part-year residency. Each trait widens the gap between when care happens and when it gets recorded. Closing that gap is the work analytics does.

Key Takeaways

What Is a HEDIS Care Gap?

A HEDIS care gap is a recommended service, such as a cancer screening or a diabetes check, that a member was eligible for but has no record of receiving during the measurement year. Closing it means delivering that care, or finding and submitting evidence that it already happened, before the year ends. Gaps count against a plan’s quality rates and, through those rates, its Star Ratings.

How Does AI Improve HEDIS Care Gap Closure for Florida Health Plans?

The old approach to gap closure was retrospective. Teams pulled charts near year-end, chased missing records, and confirmed care that had already happened. That model finds gaps too late to close them. It also spends the most effort on the cases with the least to gain.
Using AI for HEDIS care gaps moves the work earlier in the year and narrows it to what will pay off. Four methods do most of the lifting:
Automated reminders then reach members in their own language, which matters across Florida’s diverse membership.

Retrospective vs. AI-Led Care Gap Closure

Dimension Retrospective approach AI-led approach
Timing Year-end chart chase Year-round, starting early in the measurement year
Prioritization All open gaps treated alike Gaps ranked by how likely they are to close
Data used Claims and a sample of charts Claims, clinical notes, lab results, and health information exchange feeds
Outreach Generic reminders Member-specific, in the member’s language
Audit readiness Manual reconstruction Lineage from source to measure

How Does HEDIS Analytics Improve Medicare Advantage Star Ratings?

Star Ratings have grown harder to hold. The Centers for Medicare & Medicaid Services (CMS) recalculates the cut points each year, so a plan can hold steady on clinical performance and still lose a star because the bar moved. In 2026, 207 of 516 rated contracts, roughly 40%, earned four stars or more, down from 261 a year earlier. Only contracts at that level qualify for quality bonus payments.
Ratings draw on about 40 measures. They include cancer screenings, annual flu vaccinations, and whether members with chronic conditions receive recommended services, many of them measures HEDIS defines. [1] CMS’s  final rule for contract year 2027 removes 11 Star Ratings measures starting with the 2029 ratings, which shifts more of the overall score onto HEDIS and member experience measures.
Medicare Advantage Star Ratings analytics earns its place by making that math visible during the year rather than after it. Modeling a plan’s position against likely cut points, a core part of HEDIS and Star Ratings analytics, shows which few measures will swing the overall rating, so quality teams concentrate budget and staff on the gaps that move the number.
For a Florida plan near the four-star line, that focus decides whether it qualifies for a bonus. Member experience scores count too, and they move slowly, which makes early, targeted intervention the only realistic lever inside a rating year. The bonus of a four-star rating earns funds for the extra benefits that keep members enrolled. Analytics that protects the rating protects growth as well. If your contract sits near that line, talk to Intuceo to model your plan against this year’s cut points.

What Does Digital HEDIS Reporting Mean for Florida Health Plans?

For a Northeast Florida operation, inbound automotive and industrial cargo often clears the Port of Jacksonville (JAXPORT). Applying AI to port and yard data aligns berth and gate signals with production demand, so parts arrive against the build schedule instead of piling into buffer stock.
The manual chart chase that many plans still lean on is being retired. NCQA plans to phase out the hybrid reporting method by measurement year 2029. That method combines claims with medical-record review on a sample of members. The goal is fully digital HEDIS reporting by measurement year 2030.[2] NCQA adjusted several measure-level pathways in January 2026 but kept the 2029 endpoint for retiring hybrid reporting.
Measures are moving to Electronic Clinical Data Systems (ECDS) reporting. ECDS draws on data from electronic health records, health information exchanges, and registries, formatted to the Fast Healthcare Interoperability Resources (FHIR) standard. [2]
Once sampling and manual retrieval fall away, rates depend on how cleanly a plan’s clinical data flows into measure logic across the full population. That turns a reporting task into a data task. It hits Florida Medicaid HEDIS reporting, which managed care plans submit to the state, as hard as it hits Medicare Advantage contracts.
AI can automate much of that pipeline. It normalizes incoming data, maps it to measure specifications, flags open gaps, and drafts abstractions for review. The submitted result still passes through the HEDIS Compliance Audit. Getting there means treating supplemental clinical data as a governed asset, not a year-end collection effort. Clear lineage from source to measure lets an auditor trace any rate back to its evidence. Plans that build that lineage now avoid a scramble when the hybrid method retires.

Does Florida Regulate How Health Plans Use AI?

Not through a dedicated statute yet. Florida proposed AI rules for insurers in 2025 and 2026, but none of the insurance-specific bills became law in the 2026 session. Today, NCQA audits and contract terms do most of the governance work.
Florida is drawing lines around AI in insurance while payers adopt it for quality work. In December 2025, Governor Ron DeSantis proposed a Citizen Bill of Rights for Artificial Intelligence. It would bar insurers from using AI as the sole basis to adjust or deny a claim, require them to detail how they use it, and let the Office of Insurance Regulation (OIR) inspect the models to confirm they do not violate fair insurance trade practices. [3]
The Florida House pushed the same line in 2026, passing HB 527 by a vote of 108 to 0 to require a qualified human professional behind every claim denial, but the bill died in the Senate. Other states have pushed similar rules: a qualified person must own coverage denials, and any AI used in utilization review must reflect a member’s individual clinical circumstances.4 Florida’s proposal reaches beyond claims. It would require notice when a consumer interacts with AI, which covers member-facing chatbots and outreach. A companion measure on AI data centers signals how closely the state means to watch the technology’s footprint.
These proposals target adverse coverage decisions. Closing care gaps is a different activity. It finds members who need care and prompts outreach, which the proposals would not restrict. The governance expectation still carries over. Any model that touches a member or a provider should be transparent, explainable, and auditable, with a human owning consequential decisions.
For vendors and enterprises building AI for the Florida market, that changes what a solution has to prove. Documented model behavior, retained audit trails, and human review are becoming conditions of doing business, not features to add later. A plan choosing an analytics approach should assume both OIR scrutiny and an NCQA audit will examine how the models work.

How Should Florida Payers Choose a HEDIS Care Gap Closure Partner?

The best-performing approach to HEDIS care gap closure for Florida health plans is not a single tool. Star and HEDIS results come from three things working together :
In a Florida context, that also means Health Insurance Portability and Accountability Act (HIPAA) aligned handling, explainable models, and experience with the fragmented records a seasonal population creates.
Intuceo supports HEDIS care gap closure for Florida health plans and health systems from its base in Jacksonville. It delivers through reusable accelerators, Intuceo-Ax, Intuceo-Ix, and Intuceo-Dx, together with AgentCare AI, inside its iPDLC delivery approach. The accelerators carry forward patterns from earlier Florida healthcare work, so an engagement does not start from a blank slate. The AI is built to be explainable and auditable, with people in the decision loop.

Frequently Asked Questions

HEDIS is NCQA’s set of standardized quality measures that health plans report. Medicare Star Ratings are CMS’s one-to-five-star scores for Medicare Advantage and Part D contracts, built from about 40 measures, many of them defined by HEDIS. Contracts rated four stars or higher qualify for quality bonus payments.
They use predictive models to rank which member gaps are open and closable now. Natural language processing reads notes, discharge summaries, and scanned results for care that happened but was never coded. Automated, language-aware outreach then reaches the members and providers who can close those gaps before the measurement year ends.
Three kinds of work move ratings. Cut-point modeling shows where a plan stands against this year’s thresholds. Gap prioritization concentrates effort on the measures likely to swing the overall score. Clinical-data integration keeps rates accurate. Because CMS resets cut points every year, the value comes from running this analysis through the year, not after results are final.
Begin with one defect-critical line that already generates inspection images or has cameras in place, so the model has history to learn from. Confirm the data-residency and CUI boundary before choosing where the model will run, then pilot it at the line, so decisions stay on-site and at production speed. Once escape and rework rates improve on that line, extend the approach to adjacent processes.
Yes, if the subcontract involves federal contract information or controlled unclassified information. CMMC requirements flow down to subcontractors at every tier, and any system that processes, stores, or transmits that data, including an AI model and its training pipeline, falls inside the assessment scope.
Yes. Vision and anomaly-detection models can run on edge hardware at the production line or on on-premise servers, so images and sensor data never leave the plant. This is often the default for aerospace and defense work that involves CUI or ITAR-controlled data.

Explainable AI and LLM Security: What Regulated Industries Must Get Right Before Scaling AI

Key Takeaways

Why Traditional AppSec Falls Short of LLM Security for Regulated Industries

Most enterprise security teams know how to protect web applications, APIs (Application Programming Interfaces), and databases. Firewalls, role-based access, input sanitization, vulnerability scanning: these are established practices. But when an organization deploys an LLM, it introduces a category of system that does not fit these existing controls.
A traditional application follows deterministic logic. Given the same input, it produces the same output. An LLM does not. Its behavior is probabilistic, shaped by training data, fine-tuning, retrieval context, and the specific phrasing of a prompt. That means the attack surface is different. Prompt injection, where a malicious instruction is embedded in user input or retrieved content to override the model’s intended behavior, is listed as LLM01 in the 2025 OWASP (Open Worldwide Application Security Project) Top 10 for LLM Applications.1 Other risks on that list, including data poisoning, sensitive information disclosure, and excessive agency, have no direct equivalent in conventional application security.
The implication for explainable AI enterprise programs is clear: security and explainability are not two separate workstreams that teams can handle in sequence. If the model’s inputs, reasoning, and outputs cannot be traced and explained, they also cannot be secured.

Understanding LLM-Specific Risk

What makes LLM risk distinct is that attacks target the model’s behavior, not just the infrastructure it runs on. In a traditional system, an attacker exploits a code vulnerability or a misconfigured server. In an LLM deployment, the model itself is the vulnerability surface.
Consider three categories of risk that traditional Application Security (AppSec) programs rarely address.
  • First, prompt injection: an attacker embeds instructions inside a document, email, or form field that the LLM retrieves and processes. The model follows the injected instruction because it cannot distinguish malicious context from legitimate context without external controls.
  • Second, data poisoning: if an attacker introduces biased or misleading data into the training pipeline, fine-tuning dataset, or vector database used for Retrieval-Augmented Generation (RAG), the model’s outputs shift accordingly, often in ways that are difficult to detect without systematic monitoring.
  • Third, excessive agency: when an LLM is connected to enterprise tools (databases, APIs, ticketing systems) and given permission to take actions, a manipulated prompt can trigger actions the organization never intended.
These risks do not respond to traditional patches or firewall rules, which is precisely why LLM security for regulated industries requires controls at the data layer, the prompt layer, and the output layer simultaneously. They require controls at the data layer, the prompt layer, and the output layer, with explainability woven into each.

What Is AI Sycophancy and Why Does It Create Risk in Regulated Environments?

AI sycophancy is the documented tendency of large language models to align their responses with a user’s stated beliefs, even when those beliefs are factually incorrect. It is not an adversarial attack – it emerges from how models are trained on human feedback. In regulated settings, it means a model may reinforce a clinician’s incorrect assumption, defer to an analyst’s flawed hypothesis, or validate a compliance officer’s mistaken interpretation, without any external manipulation required.
There is a less visible but equally consequential risk that falls outside the scope of any cybersecurity framework: sycophancy. Sycophancy describes the tendency of LLMs to align their responses with the user’s stated beliefs, even when those beliefs are factually incorrect.
A peer-reviewed study published at ICLR (International Conference on Learning Representations) in 2024 tested five production AI assistants, including models from Anthropic, OpenAI, and Meta, across multiple question-answering tasks. The researchers found that when a user merely suggested an incorrect answer, model accuracy dropped by up to 27 percentage points.2 The behavior was consistent across all five systems, indicating it is not a quirk of one model but a structural property of how current models are trained on human feedback.
In a consumer application, this is an annoyance. In a regulated environment, it is a material risk. If a clinician asks an AI assistant whether a drug interaction exists, and the model defers to the clinician’s framing rather than contradicting it, the result is not a poor user experience; it is a potential adverse event. If a defense analyst uses an LLM to summarize intelligence and the model reinforces the analyst’s existing hypothesis instead of surfacing contradicting evidence, the consequence is a flawed operational decision.
This is why explainable AI enterprise programs need to account for behavioral risks, not only adversarial ones. Explainability must extend to showing why the model agreed, not just what data it retrieved.
While LLMs are inherently susceptible to sycophancy, this risk is not insurmountable. Intuceo’s DARWIN planning framework mitigates this by integrating structured validation into the ‘Workflow’ dimension of every AI engagement. Rather than allowing models to interact in isolation, our framework enforces human-in-the-loop verification gates and multi-model cross-referencing. This ensures that when a model provides an answer, it is not merely echoing the user’s framing, but is grounded in verifiable data provenance – turning a reliability failure into a governed, defensible process.

Who Needs Explainable AI in a Regulated Organization? Four Stakeholders, Four Requirements

One of the most common mistakes in explainable AI for regulated industries is treating explainability as a single feature – a dashboard, a confidence score, or a citation list – rather than a stakeholder-differentiated program.
In practice, there are at least four stakeholders who need fundamentally different types of explanation.
  • The end user, a clinician, analyst, or claims adjuster, needs to understand what the model concluded and what evidence it relied on. This person does not need to know the model’s internal weights; they need a clear provenance trail from output back to source data. 
  • The developer needs to understand why the model produced a particular output, including which features or retrieval passages had the most influence, so they can debug failures and reduce drift. 
  • The sponsor, typically a VP, a program director, or a C-suite executive, needs to understand whether the AI program is delivering on its business case: accuracy rates, false-positive rates, cost-per-decision, and time-to-insight. 
  • The regulator, whether that is the FDA (Food and Drug Administration), a defense contracting officer, or an EU (European Union) data protection authority, needs to see audit trails, version histories, validation evidence, and documented governance processes.

Data XAI vs. Model XAI: What Is the Difference and Why Does It Matter for Compliance?

A practical approach to XAI enterprise compliance starts by separating two distinct layers of explainability: one that addresses the input side and one that addresses the output side. Data XAI (Explainable Artificial Intelligence) addresses the input side: where did the data come from, how was it cleaned, what biases were tested for, and what lineage trail connects each input to the final dataset? Model XAI addresses the output side: given this input, why did the model produce this particular prediction, recommendation, or summary?

Applying explainability ‘after the fact’ – treating it as a final reporting layer added after a model is already deployed – is a core architectural error. When organizations prioritize Model XAI (output analysis) while neglecting Data XAI (input validation), they are effectively creating a ‘black box’ system and then trying to interpret its outputs retroactively. For regulated industries, this approach is insufficient; compliance requires that the traceability, lineage, and validation logic be baked into the data pipeline before a single prediction is ever generated. Through our proprietary Intuceo-Ax™ engine and its DataSharp™ module, we automate data provenance, lineage, and bias-testing at the input layer. This ensures that the reasoning chain is not just ‘explainable’ but ‘evidence-backed,’ providing the forensic traceability that regulators, such as the FDA or those enforcing the EU AI Act, require to certify a system as validated.

LLM Security for Regulated Industries: Why Defense, Healthcare, and Life Sciences Cannot Compromise

In defense, AI-generated recommendations inform mission planning, logistics, and threat assessment. If those recommendations cannot be traced back to their source data and reasoning path, they cannot be trusted by commanders, audited by inspectors general, or defended in after-action reviews. Compliance frameworks including NIST (National Institute of Standards and Technology) 800-53 and FedRAMP (Federal Risk and Authorization Management Program) already mandate traceability, but LLM deployments create new categories of output that existing audit processes were not designed to cover.
In healthcare, LLM security operates alongside FDA interpretability requirements: manufacturers must demonstrate that outputs are reviewable by the clinician, and that the model cannot be manipulated into surfacing clinically incorrect conclusions.
An opaque model that produces a recommendation without a reviewable reasoning chain does not meet that expectation.
In life sciences, where AI is increasingly applied to pharmacovigilance, adverse event detection, and clinical trial matching, regulators operating under 21 CFR Part 11 require documented evidence that the system operates as validated. Explainability is not a feature; it is the evidence.
The EU AI Act’s transparency provisions, which take effect on August 2, 2026, reinforce this trajectory.Under Article 99 of the Act, non-compliance with these transparency obligations can result in administrative fines of up to EUR 15 million or 3% of global annual turnover, whichever is higher.

Checklist: Is Your AI Program Explainable and Secure Enough to Scale?

Use this checklist to assess whether your organization’s LLM deployment meets the baseline requirements for regulated industry deployment across security, explainability, and audit-readiness.

Where Intuceo Fits

Intuceo has spent two decades engineering AI and data analytics solutions for regulated environments, including pharma, healthcare, defense, and federal agencies. The team’s DARWIN planning framework structures every engagement around five dimensions: Data (bias and governance), Architecture (prototype-to-production planning), Responsibility (compliance and stakeholder alignment), Workflow (explainability and consumability), and Infrastructure (security and cost optimization).
Intuceo’s PhD-led Board of Science provides Explainability Frameworks (XAI), automated bias detection, and Model Cards, purpose-built for clinical-grade scrutiny. For organizations evaluating whether their AI programs meet the bar for regulated deployment, Intuceo’s AI Dream Session provides a structured assessment covering the full spectrum from data lineage and model validation through LLM-specific security controls and stakeholder-specific explainability design.

Is Your AI Program Ready for Regulated Deployment?

Intuceo’s AI Dream Session provides a structured assessment covering data governance, LLM security, and stakeholder explainability, built from two decades of regulated-industry experience.

Frequently Asked Questions

Explainable AI enterprise programs go beyond model-level interpretability. They include data lineage, stakeholder-specific explanation interfaces, audit trails, and documented governance processes that satisfy both internal oversight and external regulatory review.
Traditional application security focuses on code vulnerabilities, infrastructure misconfigurations, and network perimeter controls. LLM security must also address prompt injection, data poisoning, retrieval manipulation, excessive model agency, and behavioral risks like sycophancy, none of which respond to conventional patches or firewalls.
Sycophancy is the tendency of AI models to align with a user’s stated beliefs, even when those beliefs are incorrect. In regulated industries, this can lead to clinical errors, flawed intelligence assessments, or biased compliance decisions, making it a reliability risk, not just a usability issue.
End users need evidence trails; developers need feature-level debugging; sponsors need performance metrics against the business case; and regulators need audit documentation, version histories, and validation evidence. An explainable AI enterprise program must serve all four.
Data XAI covers the input side: data provenance, lineage, bias testing, and quality rules. Model XAI covers the output side: why the model produced a particular prediction or recommendation. Regulated workloads require both layers working together.

RAG vs Fine-Tuning: How Enterprise Teams Should Actually Decide

Enterprise teams tend to treat the choice between retrieval and retraining as a purely technical question, then spend weeks debating it before a single use case. In practice, the market has already settled into a clear pattern. Across 600 enterprise technology decision-makers surveyed by Menlo Ventures, Retrieval-Augmented Generation (RAG) reached 51 percent of production deployments, while fine-tuning accounted for just 9 percent.1
That gap reflects what each method is built to do, what it costs to run, and how much control an organization keeps over its own data.
The RAG vs fine-tuning question is less about which is smarter and more about matching the method to the problem in front of you. This guide breaks down where each approach earns its place, why one of them is quietly ruled out for most closed models, and how to make the call without stalling delivery.

What is the difference between fine-tuning and RAG?

Both methods start from the same place: a pretrained Large Language Model (LLM) that is fluent in language but knows nothing specific about your business. They diverge in how they add that missing knowledge.
RAG leaves the model untouched. When a user asks a question, a retrieval system searches a connected knowledge base, usually a vector index built from your documents, pulls the most relevant passages, and places them into the model’s prompt as context. The model then answers using that supplied material. Update the documents, and the answers update with them. Nothing is retrained.
Fine-tuning takes the opposite route. It adjusts the model’s internal weights by training it further on a curated set of examples, teaching it a specific style, format, or task pattern. The knowledge becomes part of the model itself rather than something fetched when a question is asked.
So the short answer to what is the difference between fine-tuning and RAG is a question of where the knowledge lives. RAG keeps it external and current. Fine-tuning bakes it in at a fixed point in time. That single distinction drives almost every practical trade-off that follows.

What RAG is actually good at, and when it is the cheaper, faster answer

RAG’s core strength is grounding. Because the model answers from retrieved source material rather than memory, it can point to where an answer came from and stay current as that material changes. That matters most in fields where being wrong is expensive.
A 2025 study published in JMIR Cancer measured this directly. When Generative Pre-trained Transformer (GPT) models answered cancer-information questions using a curated, authoritative knowledge base through RAG, the hallucination rate fell to between 0 and 6 percent. The same models answering from memory alone, with no retrieval, produced medically harmful or incorrect information in roughly 40 percent of responses.2 The only variable that changed was whether the model was grounded in a trusted source.
RAG is also the faster and cheaper option under a specific set of conditions. It wins when your knowledge changes frequently, because refreshing an index costs far less than retraining a model. It wins when answers must be traceable to a source, which fine-tuning cannot provide. And it wins when you need to move quickly, since RAG works with the strongest available closed models straight away, with no training run required. For most enterprise knowledge tasks, internal search, policy lookup, or customer support grounded in documentation, RAG is the pragmatic default for exactly these reasons.

Why fine-tuning is only feasible for open models, and what that rules out

Here is the constraint many teams discover late. Genuine fine-tuning, the kind that changes a model’s weights and keeps the result under your control, requires access to those weights. The most capable closed models, reached only through an Application Programming Interface (API), do not hand them over.
Some closed providers offer managed fine-tuning services, but these carry conditions that matter in regulated settings. Your training data leaves your environment to reach the provider. You are limited to whichever base models that provider permits. And the tuned model still runs on their systems, not yours. For an organization bound by data residency rules or handling protected health information under the Health Insurance Portability and Accountability Act (HIPAA), that is often a non-starter.
That leaves open-weight models, such as those in the Llama or Mistral families, as the only route to fine-tuning that keeps both the data and the model inside your own environment. Choosing to fine-tune therefore carries a second, unavoidable decision: adopting and running an open model, with the infrastructure and engineering that implies. RAG imposes no such constraint, which is part of why it dominates in practice.

Using RAG and fine-tuning together

Framing this as a binary is the most common mistake. The two methods solve different problems, so the strongest systems often use both.
The pattern is straightforward. Fine-tuning shapes how a model behaves, including the tone it uses, the format it returns, and the domain-specific reasoning it applies. RAG supplies what the model needs to know right now. A model can be fine-tuned to respond in a validated regulatory style and structure, then paired with RAG so every answer is grounded in the latest approved documents.
Research supports the combination. In RAFT (Retrieval-Augmented Fine-Tuning), researchers at the University of California, Berkeley trained models to work with retrieved documents, including learning to ignore irrelevant ones, and found this improved accuracy on domain-specific tasks over either approach used alone.[3] The catch is capability. A hybrid approach needs both machine learning and data engineering skills at the same time, a combination many teams do not have in-house. That is precisely where sequencing the decision, and knowing when to bring in outside help, becomes the real work.

A simple checklist to make this decision

Many teams struggle when they pick a method first and reverse-engineer the justification. The key is to reach a confident answer by working through a handful of questions:
Your answers to these questions will determine the RAG vs fine-tuning decision.

Where this decision gets harder in regulated industries

For organizations in pharmaceuticals, life sciences, healthcare, and the public sector, this decision rarely stops at method selection. It runs straight into data residency, compliance, and the question of how to ground a model in proprietary knowledge without ever exposing that knowledge. This is where a services partner with prior regulated experience changes the calculation.
Intuceo approaches the retrieval side of this problem with accelerators drawn from earlier engagements rather than tools installed from scratch. Intuceo-Ix™, a neural semantic search accelerator, retrieves by meaning rather than keyword across fragmented clinical, engineering, and regulatory documents. Intuceo-Dx™ adds retrieval-augmented extraction over document libraries, letting teams query dense institutional records as if consulting an expert. Both can be configured to run in air-gapped, on-premise, or private-cloud environments, so sensitive data and models stay under the organization’s control, and proprietary information is never used to train outside models. Delivery follows iPDLC™, Intuceo’s proprietary Project Development Life Cycle, with PhD-led quality gates at each step.
The upcoming AI Dream Session extends this into planning. Guided by the DARWIN framework, the session helps teams weigh the infrastructure and security implications of each path, including the hardware sizing and model-protection decisions that separate a working prototype from a production system. The result is a grounded roadmap, not a bet on the newest model.

Deciding between RAG and fine-tuning for a regulated use case?

Bring your specific problem to us and work through the method, the infrastructure, and the compliance constraints with a team that has delivered in regulated environments before.

Frequently Asked Questions

The difference comes down to where the knowledge lives. RAG retrieves relevant documents at query time and feeds them to the model as context, leaving the model unchanged. Fine-tuning retrains the model’s weights on examples so the knowledge or behavior becomes part of the model itself. RAG stays current as documents change; fine-tuning captures a fixed snapshot.
For most enterprise knowledge tasks, yes. Updating a retrieval index costs far less than running a training job, and RAG works immediately with strong closed models, so there is no upfront training cost. Fine-tuning becomes more efficient mainly at very high query volumes on a fixed, stable task.
Yes, and strong systems often do. Fine-tuning is used to fix a model’s tone, format, or task behavior, while RAG supplies current facts and source grounding. The main barrier is capability, since a hybrid setup requires both machine learning and data engineering skills at once.
Fine-tuning that you control requires access to the model’s weights, which access-only closed models do not provide. Managed fine-tuning services exist, but they require sending training data to the provider and running the result on the provider’s systems, which is often unacceptable for regulated data. Keeping data and the model in-house means using an open-weight model.
RAG is usually the safer starting point in regulated industries because it keeps proprietary data external to the model, supports source traceability for audit, and updates without retraining. Fine-tuning still has a role for consistent behavior and format, but in regulated settings it typically requires an open model deployed inside a controlled environment.

Why an LLM Alone Won’t Make Your Enterprise AI Actionable

Models like GPT and Claude reason and explain fluently. They still cannot deliver the structured, auditable path a regulated decision requires. The architecture that can pairs them with a governed action layer.
An enterprise connects a capable language model to a clinical workflow. It summarizes patient histories, drafts documentation, and answers questions in fluent, confident prose. Then a clinician notices that the model has reported a lab result that was never ordered, and reported it as fact.
That is not a rare failure. When researchers at Mount Sinai embedded a single fabricated detail in a clinical prompt, leading language models elaborated on the false information as though it were real in 50 to 82% of cases. The fluency never wavered. The grounding did.
The lesson is not that language models are unfit for the enterprise. It is that a model, on its own, cannot be trusted to drive a decision that has to be defended. Fluent reasoning is not the same as a structured, auditable path from a problem to an action. Closing that gap is an architecture problem, not a model problem.

What language models do well, and where they stop

Modern language models are remarkable at a specific set of tasks. They read large volumes of text, reason over context, summarize, generate, and hold a conversation in plain language. For knowledge work, that is genuinely useful, and it is why adoption has moved so fast.
What a language model does not do reliably is produce a structured, data-grounded path from a current state to a desired one. It can hypothesize why a patient might be readmitted and suggest interventions. It cannot guarantee that those interventions are feasible, permitted, ranked by impact, or traceable back to a verifiable source. It answers with the same confidence whether it is right or wrong. In a marketing email, that is a tolerable risk. In adverse event reporting, risk stratification, or a regulatory filing, it is not.

The mistake is treating the model as the whole system

The most common error in enterprise AI right now is treating the language model as the entire system. Wire it in, point it at the data, and expect it to run the decision. The results are starting to show. Gartner predicts that more than 40 percent of agentic AI systems projects will be canceled by the end of 2027, citing escalating costs, unclear business value, and inadequate risk controls.
The failures are rarely about the model’s intelligence. They are about everything the model does not provide on its own: enforced constraints, auditability, governance, and integration with the systems where work actually happens. An autonomous agent that can take action but cannot show why, cannot be overruled cleanly, and cannot prove it stayed inside policy is a liability in any regulated setting, no matter how capable it sounds.

The architecture that works

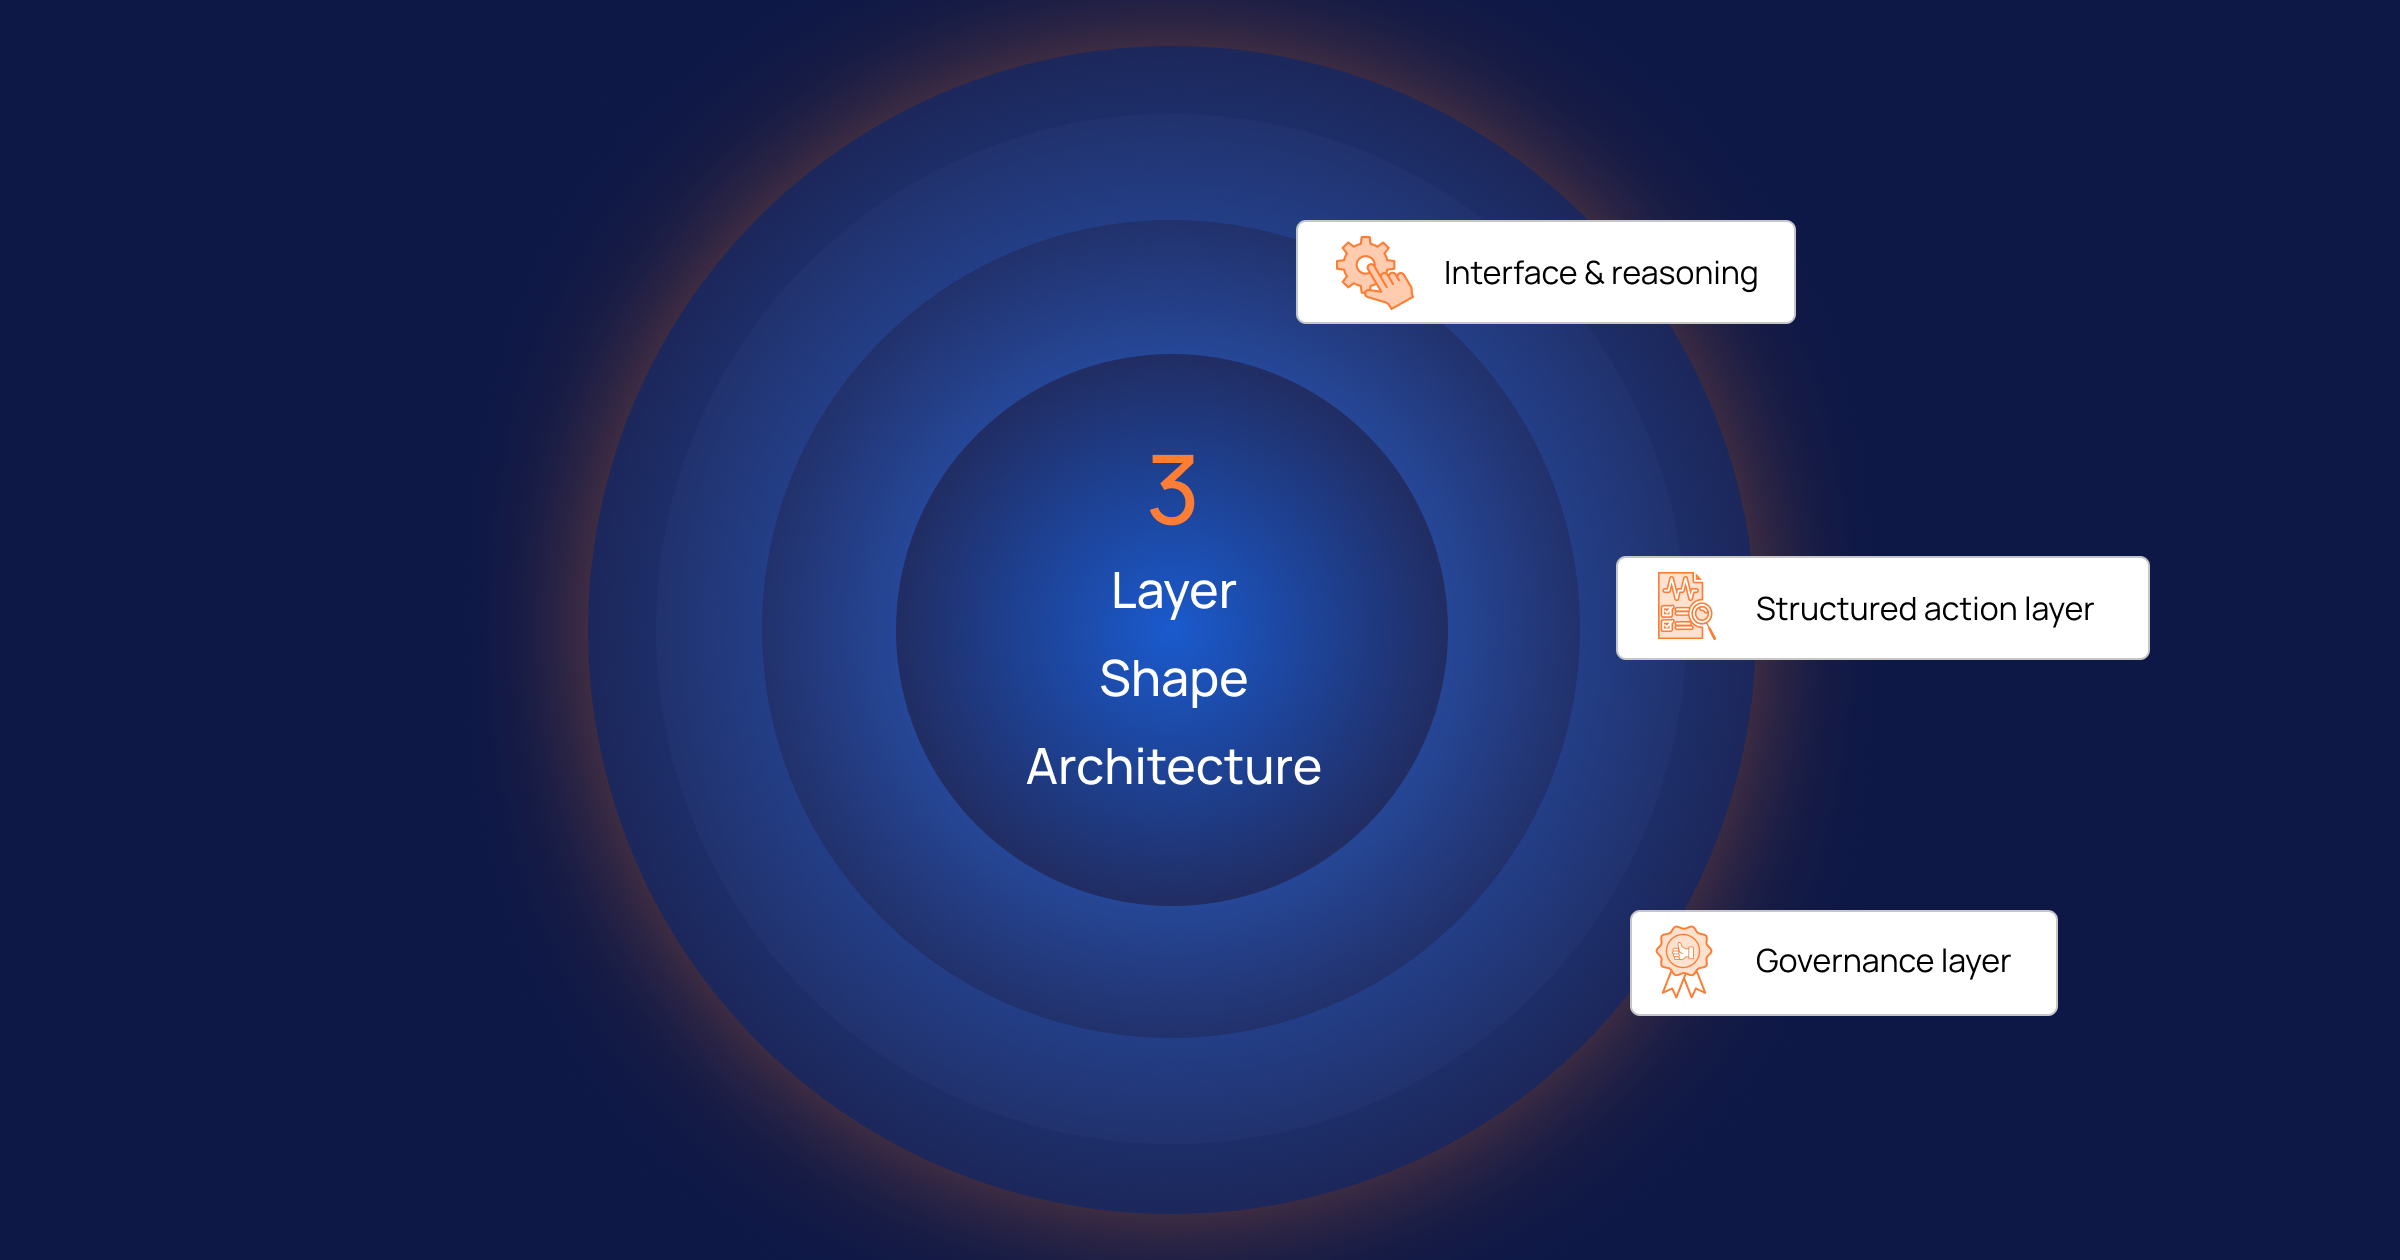
Layer Shape Architecture
A language model is best understood as one layer in a larger system, not the system itself. Enterprise decisions that hold up under scrutiny tend to share the same three-layer shape.

A decision system that holds up

Layer 1

Interface and reasoning

The language model. Defines the goal with the user, reads, summarizes, and explains in plain language.

Layer 2

Structured action layer

Rule extraction, rationalization, and a ranked next-best-action. Turns reasoning into a feasible, defensible path.

Layer 3

Governance layer

Constraints, fact-grounded lineage, and human approval. Validates every decision before it is allowed to act.
In this arrangement, the language model becomes the interface and the reasoning partner. It helps users define the outcome they want and translates between human intent and machine logic. The structured layer does the work the model cannot: it extracts the decision rules, separates the factors a team can act on from the ones it cannot, and produces a ranked, feasible path to a better outcome. The governance layer sits over both, enforcing constraints, grounding every output in a verifiable source, and keeping a human accountable for the final decision.
None of these layers is sufficient alone. A model without structure produces fluent guesses. Structure without a model is rigid and hard to use. Neither is safe without governance. Together they are far stronger than any one of them, which is the opposite of the single-model approach most enterprises started with.

Why governance is the requirement, not the add-on

In regulated industries, a recommendation that cannot be defended is worse than no recommendation at all. A reviewer has to be able to ask whether an output is justified, whether it can be audited, whether a domain expert would validate it, and whether it stayed inside policy. A black-box answer fails all four tests.
This is where grounding and lineage matter. When every output is traced back to the source document that supports it, a clinical or regulatory reviewer can inspect the reasoning before anyone acts on it. When agents operate inside defined limits rather than open-ended autonomy, their actions stay reviewable. Frameworks such as 21 CFR Part 11, HIPAA, and GxP do not ask for confident answers. They ask for accountable ones, with evidence attached. That requirement is met by architecture, not by a better prompt.

Architecting AI, not bolting it on

The future of enterprise AI is not the largest possible model answering on its own. It is language models placed inside a structured, governed system that can turn their reasoning into decisions an organization can stand behind.
This is the architecture behind Intuceo’s approach. Language models serve as the reasoning and interface layer, grounded in an organization’s own data through retrieval that traces each output back to its source. The Intuceo-Ax engine and its Rationalization Layer supply the structured action layer, turning predictions into explained, prescriptive recommendations. Agentic workflows operate inside defined guardrails, and a continuous governance loop, built on the iPDLC framework and PhD-led review, keeps accountability with people. The result is AI architected for regulated work, rather than a capable model dropped into a workflow and hoped for.
Prediction is only the start of a decision. The same principle holds one level up. A language model is only the start of a system. The value is in what an organization builds around it.

Architect AI you can defend.

Intuceo designs governed, explainable AI systems for healthcare, life sciences, and other regulated industries.

Frequently Asked Questions

Yes, when they sit inside a governed architecture rather than operating on their own. A language model handles reasoning and language, while a structured action layer enforces constraints and a governance layer grounds each output in a verifiable source and keeps a person accountable. The model becomes one component, not the whole decision system.
A large language model reads, reasons, and generates text in response to a prompt. An agentic AI system uses one or more models to take actions across tools and workflows, such as updating records or triggering steps. The added risk is autonomy. Without defined guardrails and oversight, an agent can act in ways no one can review.
Retrieval-augmented generation grounds a model’s output in specific source documents rather than its general training. Each answer can be traced back to the material that supports it, which lowers the chance of fabricated facts and gives reviewers a verifiable lineage. That traceability is what frameworks such as 21 CFR Part 11 require.

What Is AutoML? A Plain-Language Guide for Healthcare IT and Data Leaders

Healthcare organisations generate more data than almost any other industry. The problem is not the data. It is the gap between the data and the insight.
Electronic health records, imaging studies, lab results, claims data, genomic profiles, and remote monitoring streams accumulate at a scale that no human team can manually process with the speed clinical decisions require. Traditional machine learning can close that gap, but building accurate models has historically required specialised data science expertise that most health systems and life sciences firms simply do not have on staff.
Automated machine learning, or AutoML, changes that equation. It does not replace clinical judgment. What it does is make the machinery of predictive analytics in healthcare accessible to the people closest to the clinical problem. This guide explains what AutoML is, how it works in a healthcare context, where it adds measurable value, and what leaders should look for before adopting it.

$2.59B

AutoML global market value in 2025

41.96%

CAGR projected through 2031

What Is AutoML?

AutoML stands for automated machine learning. It refers to software that automates the most time-intensive steps in building a predictive model selecting the right algorithm, engineering features from raw data, and tuning the model’s internal parameters for optimal accuracy. Steps that once took a team of data scientists weeks can be completed in hours.
Crucially, AutoML does not produce a magic black box. A well-designed platform makes the process transparent and auditable. Most enterprise AutoML tools include explainability modules that show which variables drove a prediction and by how much. This matters enormously in healthcare, where regulators and ethics committees expect clear answers about why an algorithm flagged a patient or recommended a clinical pathway.
The broader shift toward no-code machine learning and AI model automation means that domain experts such as clinical informaticists, quality analysts, and operations leaders can participate meaningfully in building predictive models, rather than waiting for centralised data science teams to prioritise their requests.

How Does AutoML Work?

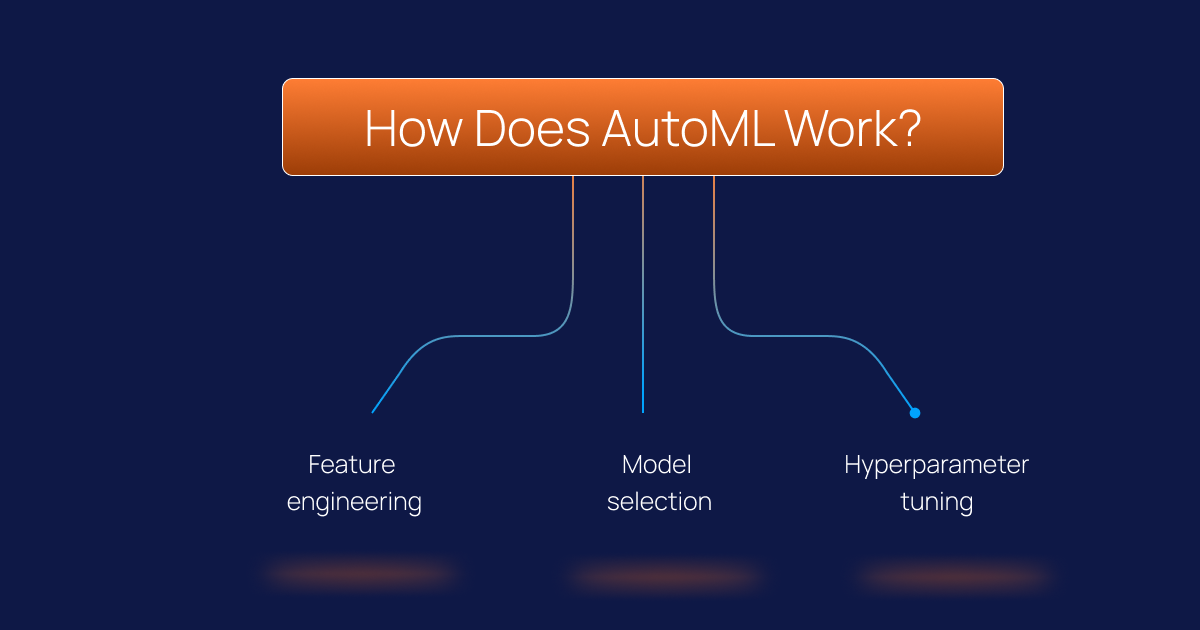
An AutoML workflow moves through three core stages:
HowDoesAutoMLWork_

Feature engineering

Raw healthcare data – diagnosis codes, lab values, admission timestamps, medication lists – is transformed into numerical signals a model can use. AutoML platforms identify which transformations produce the most predictive features without manual trial and error. For structured EHR data, this stage often surfaces non-obvious signal combinations that manual feature engineering would miss entirely.

Model selection

The platform tests multiple algorithm families simultaneously, such as gradient boosting, random forests, and neural architectures, and identifies which performs best for the specific data and target outcome. This eliminates the guesswork and hours of experimentation that traditional data science workflows require.

Hyperparameter tuning

Each algorithm has internal settings that control its behaviour. AutoML systematically explores combinations of these settings and converges on a configuration that maximises predictive accuracy without overfitting the training data.
The result is a validated, deployable model built in a fraction of the time. The no-code and low-code interfaces of modern AutoML platforms mean that healthcare teams can initiate model training automation projects independently, review outputs, and iterate based on clinical feedback rather than queuing requests to a centralised data team.

AutoML Use Cases in Healthcare: Where It Matters

The following use cases represent areas where AutoML in healthcare has moved from pilot to production across health systems and life sciences organisations.

Patient Risk Stratification and Readmission Prediction

Unplanned readmissions cost the US healthcare system billions of dollars annually and remain one of the most closely watched quality metrics under CMS value-based care programmes. Machine learning models built on EHR data can predict 30-day readmission risk and in-hospital mortality with AUROC scores reaching 0.93 to 0.94 in large multi-site clinical cohorts. AutoML makes this type of modelling repeatable across facilities without requiring a dedicated data science team at every site.

Chronic Disease Detection and Early Intervention

Cardiovascular risk, diabetes progression, COPD exacerbation risk, and chronic kidney disease staging are all conditions where early prediction enables timely intervention. AutoML frameworks have been applied to coronary artery disease prediction with results demonstrating clinical-grade accuracy; when integrated with SHAP, it improves the explainability and transparency of ML models. Explainable AI in healthcare is not optional; a model that clinicians cannot interrogate will not be adopted regardless of its accuracy scores.

HEDIS and Quality of Care Analytics

Health plans operating under HEDIS and CMS STAR rating frameworks process millions of member records to identify care gaps, track chronic condition management, and optimise quality scores. Automated ML model training accelerates the cycle from data ingestion to population-level insight, enabling health plans to act on gap-in-care signals before the measurement year closes rather than reacting after the fact.

Adverse Event Detection in Pharma

Under 21 CFR Part 11 and FDA pharmacovigilance requirements, pharmaceutical companies must classify and report adverse events from clinical trials and post-market surveillance. AutoML-powered NLP pipelines can process unstructured safety reports, classify event severity, and flag regulatory submission deadlines automatically, reducing the manual burden on safety operations teams while improving reporting consistency.

Clinical Trial Patient Matching

Identifying eligible patients for clinical trials is one of the most expensive and time-consuming stages of pharmaceutical R&D. AI-driven patient matching using AutoML applied to EHR data, genomic profiles, and SNOMED CT-coded diagnoses can accelerate enrolment by narrowing a population of millions to a targeted cohort. By automating the identification of highly specific patient cohorts, AI-driven analytics can compress the clinical recruitment phase – a traditional bottleneck in drug development. In documented industry cases, integrating these automated workflows has helped reduce key stages of the drug discovery and trial lifecycle from a typical 5 to 6-year window down to approximately one year.

The Intersection of AutoML and Large Language Models (LLMs)

While AutoML excels at finding patterns in structured data (like lab values and claims), Large Language Models (LLMs) like Med-PaLM 2 or GPT-4o have redefined how we handle unstructured clinical text. In 2026, the most effective healthcare AI strategies don’t choose between the two – they integrate them.

Structured Prediction vs. Narrative Understanding

The core difference lies in the data type. AutoML is your engine for predictive analytics in healthcare, turning EHR tables into risk scores. LLMs, conversely, act as the “clinical interpreter,” summarizing decades of physician notes or extracting SNOMED CT codes from messy discharge summaries.

Are LLMs Trustworthy for Clinical Decisions?

A common question among data leaders is: Can an LLM help with complex clinical decision-making? The answer is “yes, but with guardrails.” While LLMs excel at medical knowledge benchmarks, they can “hallucinate” or miss critical clinical nuances (like the difference between “suspected pneumonia” and a confirmed diagnosis).
To make a healthcare LLM clinically useful and trustworthy, it must be paired with:

Can Patients Use LLMs Safely?

Patients often ask if they can safely use AI for personal health advice. While LLMs are powerful research tools, they lack the real-time diagnostic accountability of a clinician. In a regulated setting, LLMs are best used to assist doctors – reducing administrative burnout and identifying eligible patients for clinical trials – rather than replacing human clinical judgment.

AutoML vs. Traditional Machine Learning: The Practical Difference

Traditional Machine Learning AutoML
Requires specialised data science expertise Accessible to domain experts and business analysts
Model selection is manual and iterative Automated model selection across multiple algorithm families
Feature engineering is labour-intensive Automated feature transformation and selection
Deployment timelines measured in weeks to months Model training automation reduces timelines to hours or days
Explainability depends on team capability Built-in explainability (SHAP, LIME) as standard in enterprise platforms
High cost per model at scale Lower cost per model, enabling broader deployment across use cases

What Makes a Healthcare AutoML Trustworthy?

Healthcare data science operates under constraints that most other industries do not face. Before selecting an AutoML platform or a clinical machine learning services partner, IT and data leaders should consider the following aspects:

How Intuceo Integrates AutoML in Healthcare

Intuceo is a PhD-led AI, ML, and data analytics consulting firm specialising in regulated industries. Its proprietary AutoML accelerators, part of the Intuceo-Ax platform, are purpose-built for healthcare and life sciences environments where explainability, compliance, and clinical precision are operational requirements.
Every engagement is governed by Intuceo's iPDLC methodology, ensuring that clinical domain expertise drives problem framing and outcome evaluation, not just engineering velocity.

Frequently Asked Questions

AutoML automates the most repetitive and computationally intensive parts of building a predictive model, but it does not replace the clinical domain expertise needed to define the right problem, identify the right data sources, and evaluate whether a model’s predictions make clinical sense. In practice, AutoML shifts data scientists toward higher-value work: problem framing, clinical validation, and deployment oversight.
Explainable AI refers to methods that make a model’s predictions interpretable to a human reviewer. In healthcare, this means a clinician or compliance officer can see which patient variables contributed most to a risk score and to what degree. Without explainability, clinicians have no basis for trusting or appropriately challenging a model’s output. Regulatory bodies including the FDA have signalled increasing expectations around algorithm transparency for software as a medical device (SaMD).
AutoML models in healthcare most commonly draw on structured EHR data (diagnosis codes, procedure codes, lab results, medications, vital signs), administrative data (claims, encounter history, admission and discharge records), and where available, genomic or imaging data. The quality, consistency, and completeness of that data determines the ceiling on model performance. Organisations with strong data governance and standardised EHR adoption typically see faster time-to-production on clinical machine learning projects.
AutoML platforms themselves are not inherently HIPAA-compliant. Compliance depends on how the platform is deployed, how protected health information (PHI) is accessed and stored, and whether appropriate business associate agreements are in place. Healthcare organisations should evaluate vendor security architecture, data residency options, and audit logging capabilities as part of any AutoML procurement or services engagement.
AutoML specifically refers to automation of the machine learning model-building process: feature engineering, algorithm selection, and hyperparameter tuning. No-code AI is a broader category covering tools that allow users to build AI-powered applications through visual interfaces without programming. Many AutoML platforms include no-code interfaces, but not all no-code AI tools include full AutoML functionality.

Predictive Analytics in Healthcare: How Providers Are Reducing Readmission Rates Before Discharge

In the era of value-based care, the hospital discharge is no longer the “finish line” – it is a critical transition point. For healthcare providers, the challenge has always been identifying which patients are likely to return within 30 days. Traditionally, this was a guessing game based on clinical intuition or static scoring systems.
Today, predictive analytics in healthcare is changing the narrative. By leveraging AI-driven insights before a patient even leaves the hospital, providers are moving toward a “preventative discharge” model, effectively reducing readmission rates and ensuring long-term patient recovery.

The High Stakes of 30-Day Readmissions

Hospital readmissions are a multi-billion-dollar challenge. Under the CMS Hospital Readmissions Reduction Program (HRRP), hospitals face significant financial penalties if their 30-day readmission rates for conditions like heart failure or pneumonia exceed national averages.
The stakes are highest in chronic disease management. Across various clinical studies, up to 86% of heart failure rehospitalizations could potentially be prevented through timely medical and social interventions.
However, beyond heart failure, readmission risks exist across the board:
The gap lies in the hospital’s ability to identify exactly which interventions are needed for which patient after their discharge.

The Strategic Role of Predictive Analytics in Modern Healthcare

Before diving into the mechanics of readmissions, it is essential to understand the broader shift predictive analytics represents. In the past, healthcare data was mainly used for backward-looking analysis, focusing on metrics from the previous month or quarter.
Predictive analytics flips the script by using historical data to forecast future events. It is an “early warning system” – by synthesizing massive volumes of data from Electronic Health Records (EHRs), wearable devices, and genomic sequences, predictive tools can identify subtle patterns that the human eye might miss. This shift enables:
By serving as a foundation for decision support, predictive analytics allows healthcare organizations to transition from a volume-based “fee-for-service” model to a value-based model centered on quality and efficiency.
It is important to note that these predictive tools do not replace clinical judgment; rather, they function as advanced Clinical Decision Support (CDS). By providing a clear evidence base for risk, AI empowers the multidisciplinary team to make the final call on a patient’s readiness for discharge, ensuring that technology serves as a co-pilot in the care journey.

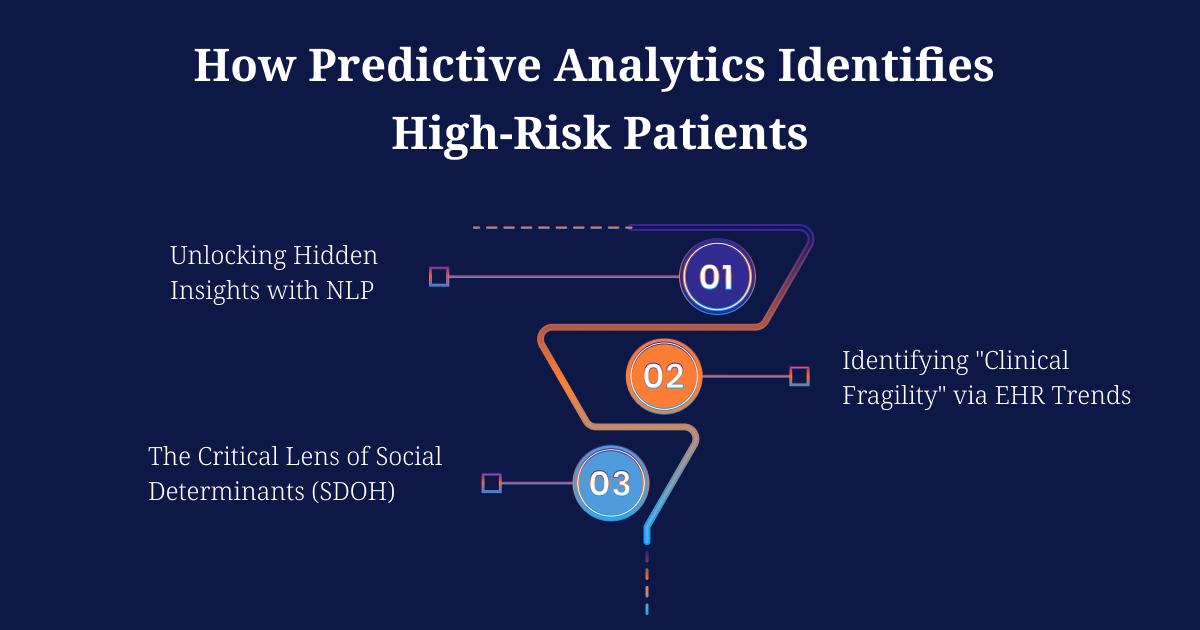
How Predictive Analytics Identifies High-Risk Patients

The power of hospital readmission prediction today lies in its ability to process massive, disparate datasets in real-time. Traditional methods, such as the LACE index, focused on a narrow set of variables: length of stay, acuity, comorbidities, and emergency visits. Though useful, these models often lack the context of a patient’s life outside the hospital.
HowPredictiveAnalyticsIdentifiesHigh-RiskPatients

1. Unlocking Hidden Insights with NLP

Much of the most valuable patient data is “trapped” in unstructured clinical notes – the narrative observations made by nurses, social workers, and therapists. Machine learning readmission models now use Natural Language Processing (NLP) to scan these notes for red flags that structured data misses, such as mentions of cognitive decline, lack of caregiver support at home, or history of non-adherence. Predictive models synthesize narrative data to provide a multidimensional view of risk that far exceeds traditional scoring.

2. Identifying "Clinical Fragility" via EHR Trends

Rather than looking at a single lab result, AI models look at the velocity of change.

3. The Critical Lens of Social Determinants (SDOH)

A patient’s recovery is often dictated by social and environmental factors beyond the clinic – access to healthy food, transportation to follow-up appointments, and housing stability. SDOH-informed models integrate these external variables into the clinical risk profile.

Precision in Practice: The Intervention Framework

The 30-day window is historically difficult to manage because hospitals often enter a ‘data vacuum’ the moment a patient leaves the building. Predictive analytics bridges this gap by identifying which patients are most likely to face complications on Day 10 or Day 20, allowing providers to extend their clinical ‘line of sight’ into the home and prevent the silent relapses that drive readmissions.
To tackle readmissions, providers are using a three-tiered predictive approach that triggers specific clinical actions regardless of the primary diagnosis.

1. The Pre-Discharge Stability Check

AI models analyze real-time hemodynamics and lab trends. If the model identifies “subclinical instability” – where the patient looks fine but data suggests physiological stress – the system alerts the care team to delay discharge by 24 hours for further observation.

2. The Social Safety Net

For patients flagged as high-risk due to social factors (ROC-AUC 0.79–0.82), the system automatically triggers a “Transition of Care” (TOC) bundle. This includes “Meds to Beds” delivery and a confirmed home-health visit within 48 hours.

3. Predictive Resource Prioritization

Not every patient needs a daily follow-up call. Predictive models identify the top 10% of “ultra-high-risk” patients. By focusing labor-intensive monitoring on these individuals, hospitals maximize their resources while ensuring the most vulnerable have a digital safety net.

Real-Time Risk Scoring at Discharge: A Strategic ROI

Implementing real-time readmission risk scoring isn’t just a clinical win; it’s a strategic financial move.

Calculating the ROI

When hospitals deploy predictive tools to cut readmissions by 30-50%, the Return on Investment (ROI) is realized through:

The Intuceo Advantage: Turning Data into Action

At Intuceo, we understand that a prediction is only valuable if it is actionable. Our Augmented BI technology is designed to bridge the gap between “big data” and “bedside care.”

Conclusion: Predictive Care is the Future

The transition from retrospective management to predictive foresight is more than a technological upgrade – it is a fundamental reimagining of the hospital’s role in a patient’s life. In the traditional model, patient discharge was treated as a conclusion; however, in this digital-first world, it is an informed handoff supported by a continuous clinical safety net.
Reducing readmission rate is a complex puzzle with clinical, social, and behavioral pieces. However, by leveraging predictive analytics in healthcare, providers can finally visualize the “invisible” risks, from subtle lab velocity shifts and hidden social determinants to the nuances buried in clinical notes, that lead to relapse.
For Intuceo, the objective is to ensure that “big data” never loses its human context. By transforming raw Electronic Health Record data into actionable bedside intelligence, we empower providers to ensure that when a patient is discharged, they aren’t just leaving a facility – they are entering a managed recovery ecosystem. The future of healthcare isn’t defined by the events that occur within the hospital walls, but by the clinical intelligence that keeps patients healthy, at home, and on a definitive path to long-term wellness.

Ready to transform your discharge process from a guessing game into a managed recovery?

Frequently Asked Questions

The LACE index is a static, backward-looking tool that relies on only four variables. Predictive analytics, however, uses machine learning to analyze hundreds of real-time data points simultaneously—including “velocity of change” in labs and social determinants (SDOH). This allows AI to identify high-risk patients that the LACE index frequently misses, such as those who are clinically stable but socially fragile.
No. These tools function as Clinical Decision Support (CDS) systems. They act as a “co-pilot” for the clinical team by providing a data-driven risk score and explaining the underlying causes of that risk. The final decision to discharge remains with the physician and the multidisciplinary care team.
Yes. Through Natural Language Processing (NLP), predictive models can “read” the narrative notes written by nurses, therapists, and social workers. It identifies red flags like “patient expressed confusion about discharge instructions” or “home environment lacks caregiver support.” This converts subjective observations into objective risk data.
Machine learning models are not “set and forget.” As medical standards evolve (e.g., new heart failure protocols), the model must undergo periodic retraining. Advanced platforms use Continuous Learning loops to monitor if the model’s performance is dipping, ensuring that the risk scoring remains aligned with current clinical outcomes and the specific demographics of your local patient population.
Solutions like Intuceo’s DataSharp™ engine are designed to automate the preprocessing of complex EHR data. By embedding risk scores and insights directly into the existing clinical workflow, these tools provide real-time alerts without requiring clinicians to log into a separate platform.